
Introduction
A trauma centre treats the most serious injuries, where minutes decide outcomes. So its equipment is built for speed and for the sickest patients. It centres on resuscitation bays, rapid imaging, fast theatre access, and the means to manage major bleeding. Setting one up means equipping trauma bays for immediate care, linking them tightly to CT and theatre, and being ready for anything that arrives.
This guide covers the full trauma centre equipment list by area. It then walks through the infrastructure, the planning sequence, and the approval and compliance points. Use it for a new centre, an upgrade, or added trauma capacity. It focuses on the equipment and readiness decisions. Where clinical, imaging and estates input is essential, it says so.
What sets a trauma centre apart is speed under pressure. A major-trauma patient can be minutes from death on arrival. So everything is arranged to act at once. Resuscitation bays hold airway, breathing and circulation equipment ready to go. Imaging, especially CT, sits close so diagnosis is fast. Theatre and interventional radiology are on call for damage-control surgery. Blood and major-haemorrhage provision are immediate. The centre is designed so a trauma team can assess, image, transfuse and operate without losing time. Every second is designed out.
In practice, the decisions that matter most are about readiness, proximity and flow. Trauma bays must be fully stocked and checked, so nothing is missing when a patient arrives. Rapid CT close to the bays saves the minutes that matter, so its location is planned, not left to chance. Major-haemorrhage and transfusion provision must be immediate. Standardise equipment with the emergency department and theatres, so teams move seamlessly. Plan the bays, imaging, theatre and blood together, and the centre is ready when it counts. In trauma, readiness is everything.
The short version — what every trauma centre is built around
Strip it back, and a trauma centre needs three things. Resuscitation bays ready for the sickest patients. Rapid imaging and theatre access. And immediate provision for major bleeding.
-
Resuscitation bays — airway, breathing and circulation equipment ready at once.
-
Rapid imaging & theatre — CT close by, with fast theatre and interventional access.
-
Major haemorrhage — immediate blood and transfusion provision for serious bleeding.
Trauma centre equipment by area
-
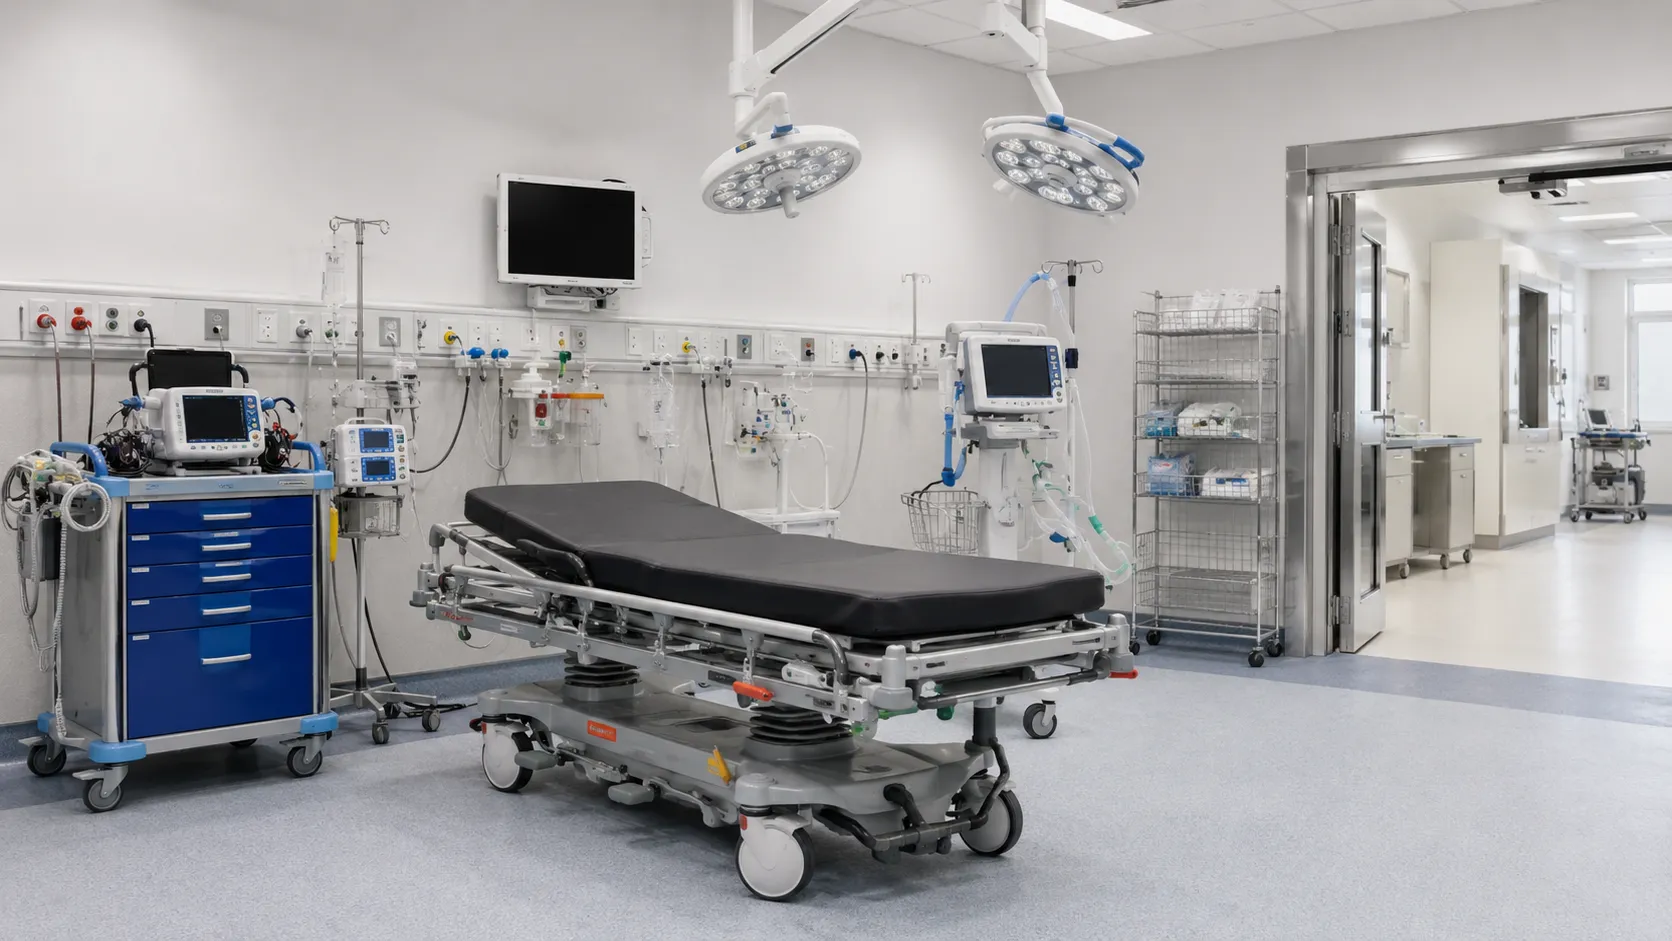
Resuscitation bays. Fully equipped trauma bays with airway, breathing and circulation kit. Everything is ready and checked, so the team acts the moment a patient arrives. Nothing is hunted for.
-
Airway & breathing. Advanced airway equipment, ventilators and oxygen at every bay. Serious trauma often threatens the airway first. So an airway kit sits ready at every bay.
-
Monitoring & circulation. Multi-parameter monitors, rapid infusers and access equipment. Unstable patients need close watching and fast resuscitation. Rapid infusers replace blood volume quickly.
-
Rapid imaging. CT close to the bays, plus portable X-ray and ultrasound. Fast imaging guides life-saving decisions in minutes. CT close to the bays saves those minutes.
-
Theatre & interventional access. Fast access to an operating theatre and interventional radiology. Damage-control surgery and bleeding control cannot wait. Theatre and radiology stay on call.
-
Major haemorrhage. Immediate blood, rapid transfusion and warming, and a major-haemorrhage response. Serious bleeding is a leading cause of death. Blood is ready before it is needed.
-
Trauma team & handling. Equipment for a trauma team to work together, plus transfer and handling aids. Moving unstable patients safely matters.
-
Infrastructure. Piped gases, resilient power, and a layout linking bays, CT and theatre closely. Proximity saves minutes.
Trauma centre equipment checklist
|
Section |
Equipment |
Notes |
|
Resus bays |
Fully stocked trauma bays |
Ready and checked |
|
Airway |
Advanced airway; ventilators; oxygen |
Airway first |
|
Circulation |
Monitors; rapid infusers; access |
Watch and resuscitate |
|
Imaging |
Rapid CT; portable X-ray/ultrasound |
Decisions in minutes |
|
Theatre |
Theatre + interventional access |
Cannot wait |
|
Haemorrhage |
Blood; rapid transfusion; warming |
Leading cause of death |
|
Team/handling |
Trauma-team kit; transfer aids |
Move safely |
|
Infrastructure |
Gases; power; bays-CT-theatre close |
Proximity saves minutes |
Scale each area to your role and caseload. A trauma unit stabilising and transferring and a major trauma centre doing definitive care differ widely in imaging, theatre and blood provision. Your role decides the kit.
Planning a trauma centre?
We'll help you equip it end-to-end. Tell us your role, caseload, budget and market. We'll build the equipment list, balance new and refurbished units, and make sure everything is compliant and supported.
No pressure, no obligation. → Talk to the team
What else does setting up a trauma centre involve
-
Readiness is everything. A trauma team cannot pause to find equipment. So bays are fully stocked and checked, and readiness shapes the centre as much as the equipment list. A checked bay saves lives.
-
Proximity saves minutes. Rapid CT and fast theatre access decide outcomes. So the layout links bays, imaging and theatre closely, because distance costs time a patient may not have.
-
Major haemorrhage provision. Serious bleeding is a leading cause of trauma death. So immediate blood, rapid transfusion and warming are core, not optional.
-
Working with the wider hospital. Trauma draws on imaging, theatres, critical care and blood. So the centre is planned to work with the whole hospital, not in isolation. Trauma is a team sport.
-
Consumables, staffing and service. Airway, transfusion and monitoring consumables, a trained trauma team, and service contracts all shape the running model. The purchase is only the start.
Setting up a trauma centre, step by step
-
Define your role and caseload. Decide whether you stabilise and transfer, or provide definitive major-trauma care.
-
Confirm infrastructure and layout. Link bays, CT and theatre closely, with gases and power. Start works early.
-
Build the equipment list by area, sized to your role, with resuscitation, imaging and haemorrhage provision throughout.
-
Decide new versus refurbished per item. Plan consumable and service contracts alongside.
-
Install, commission and test everything. Set up readiness and the trauma response, and train the team before go-live.
Readiness, layout and team training take time. Build them into the schedule, so the centre can respond safely from day one rather than only being equipped.
Budget and procurement
Trauma care is equipment- and readiness-intensive. So the purchase price is only part of the story. Bays, imaging, theatre access and blood provision all carry running and service costs. A common approach is to buy new for high-throughput core units and certified refurbished for ancillary equipment. Because these are regulated devices, check the device risk class and the certification for your market. Match imaging, theatre and blood provision to your role. A trauma unit and a major trauma centre are then each equipped for the care they actually provide.
Approval and accreditation by region
|
Region |
Regulator |
Device requirement |
|
United Kingdom |
UKCA mark (CE accepted to 2028–2030) |
|
|
European Union |
CE marking under the MDR |
|
|
United States |
FDA clearance or approval |
|
|
Gulf (GCC) |
SFDA & GCC bodies |
National registration / GCC conformity |
|
South Africa |
Medical device licensing |
Trauma and resuscitation devices are regulated, so confirm each is approved for your market. Trauma equipment must be immediately ready for the sickest patients, so readiness and servicing matter alongside device approval. For quality standards and clinical guidance, the World Health Organisation and NICE are useful references. If you're equipping a trauma centre, our buyer hub sets out how to purchase with confidence.
More from Business
-
Buyers — source a full trauma centre equipment package for your hospital.
-
Suppliers — list your equipment and reach buyers worldwide.
-
Advertise — promote your products and services to a clinical audience.
-
Business overview — explore everything MediGear offers healthcare organisations.
Disclaimer
This article is for general information only. It is not clinical, medical, procurement, engineering or regulatory advice. Trauma centre design, equipment, imaging, readiness and safety requirements vary by country, role and facility, and change over time. The checklist is a planning aid, not a specification. Always work with qualified clinical, biomedical, facilities and procurement professionals. And confirm every device is approved for your market — for example, UKCA, CE, FDA, SFDA/GCC or SAHPRA. Requirements change, so check the current position before you buy. medigear.UK accepts no liability for actions taken on this content.
Equip your trauma centre end-to-end.
From resuscitation bays and rapid imaging to theatre access and major-haemorrhage provision, we help hospitals across the UK, Europe, the US, the Gulf and South Africa build trauma centres — compliant, supported and ready.
Frequently Asked Questions
A trauma centre needs fully equipped resuscitation bays with airway, breathing and circulation kit, advanced airway equipment and ventilators, multi-parameter monitors and rapid infusers, and rapid imaging, especially CT close to the bays. It also needs fast theatre and interventional access, and immediate major-haemorrhage and transfusion provision. Everything is arranged for speed.
The main areas are resuscitation bays, airway and breathing, monitoring and circulation, rapid imaging, theatre and interventional access, major haemorrhage provision, trauma-team and handling equipment, and the supporting infrastructure. These are planned together, because a major-trauma patient may need all of them within minutes.
Costs depend on your role, the imaging involved and whether you provide definitive major-trauma care, so there is no single figure. Trauma care is equipment- and readiness-intensive. Weigh the purchase price against running and service costs over the life of each system rather than the upfront price alone.
Yes, for many items. Certified refurbished imaging and monitoring can be sensible where fully supported and reliable, while high-use resuscitation kit is often bought new. Every device must be approved for your market, immediately ready and fully supported, whether new or refurbished.
It varies with the role and whether imaging and theatre works are needed, but planning, equipping, commissioning and training typically take several months. The close layout between bays, CT and theatre, readiness and team training are the parts most often underestimated.
A trauma centre needs piped medical gases, resilient power, and a layout that links resuscitation bays, CT and theatre closely, with immediate blood provision. This proximity and readiness matter as much as the clinical equipment, because in major trauma the minutes saved by a good layout can decide the outcome.