
Introduction
An endoscopy unit uses flexible scopes and cameras to look inside the body and treat what it finds, so its equipment is built around the scopes, the imaging stacks that drive them, and the reprocessing that keeps them safe to reuse. Setting one up means fitting out procedure rooms with endoscopes and stacks, a decontamination area that reprocesses scopes rigorously, and the monitoring and sedation that patients need.
This guide sets out the full endoscopy unit equipment list by area, the surrounding infrastructure and safety, the planning sequence, and the approval and compliance points — for a new unit, an expansion, or added endoscopy capacity, wherever your hospital operates. It focuses on the equipment and reprocessing decisions, and flags where clinical, decontamination and estates input is essential.
What sets endoscopy apart from most procedure units is that its main instruments are reused, and reused on the inside of the body, so decontamination is not a supporting service but a central one. A flexible endoscope is a delicate, expensive device with long internal channels that must be cleaned and disinfected to a high standard between every patient, which is why an endoscopy unit is built around automated reprocessing, drying and controlled storage as much as around the scopes and stacks themselves. The procedure side and the decontamination side are planned together, with a clear flow that keeps dirty and clean scopes apart.
In practice, the decisions that matter most are about reprocessing, scope numbers and traceability rather than the stacks alone. Too few scopes for the reprocessing cycle time becomes the bottleneck that limits how many patients a unit can see, so scope numbers, washers and drying cabinets are sized together. Tracking each scope through decontamination and to the patient supports safety, recall and audit. Standardising scopes and stacks across rooms simplifies training, servicing and the stock of accessories, while planning the dirty-to-clean flow from the outset keeps every procedure safe.
The short version — what every endoscopy unit is built around
Strip it back, and an endoscopy unit needs three things — scopes and stacks to see and treat, rigorous reprocessing to make scopes safe to reuse, and monitoring for patients under sedation.
-
Scopes & stacks — flexible endoscopes and the imaging stacks that drive them.
-
Reprocessing — automated washer-disinfectors, drying and storage that make scopes safe to reuse.
-
Patient monitoring & sedation — monitoring and recovery for patients undergoing procedures under sedation.
Endoscopy unit equipment by area
-
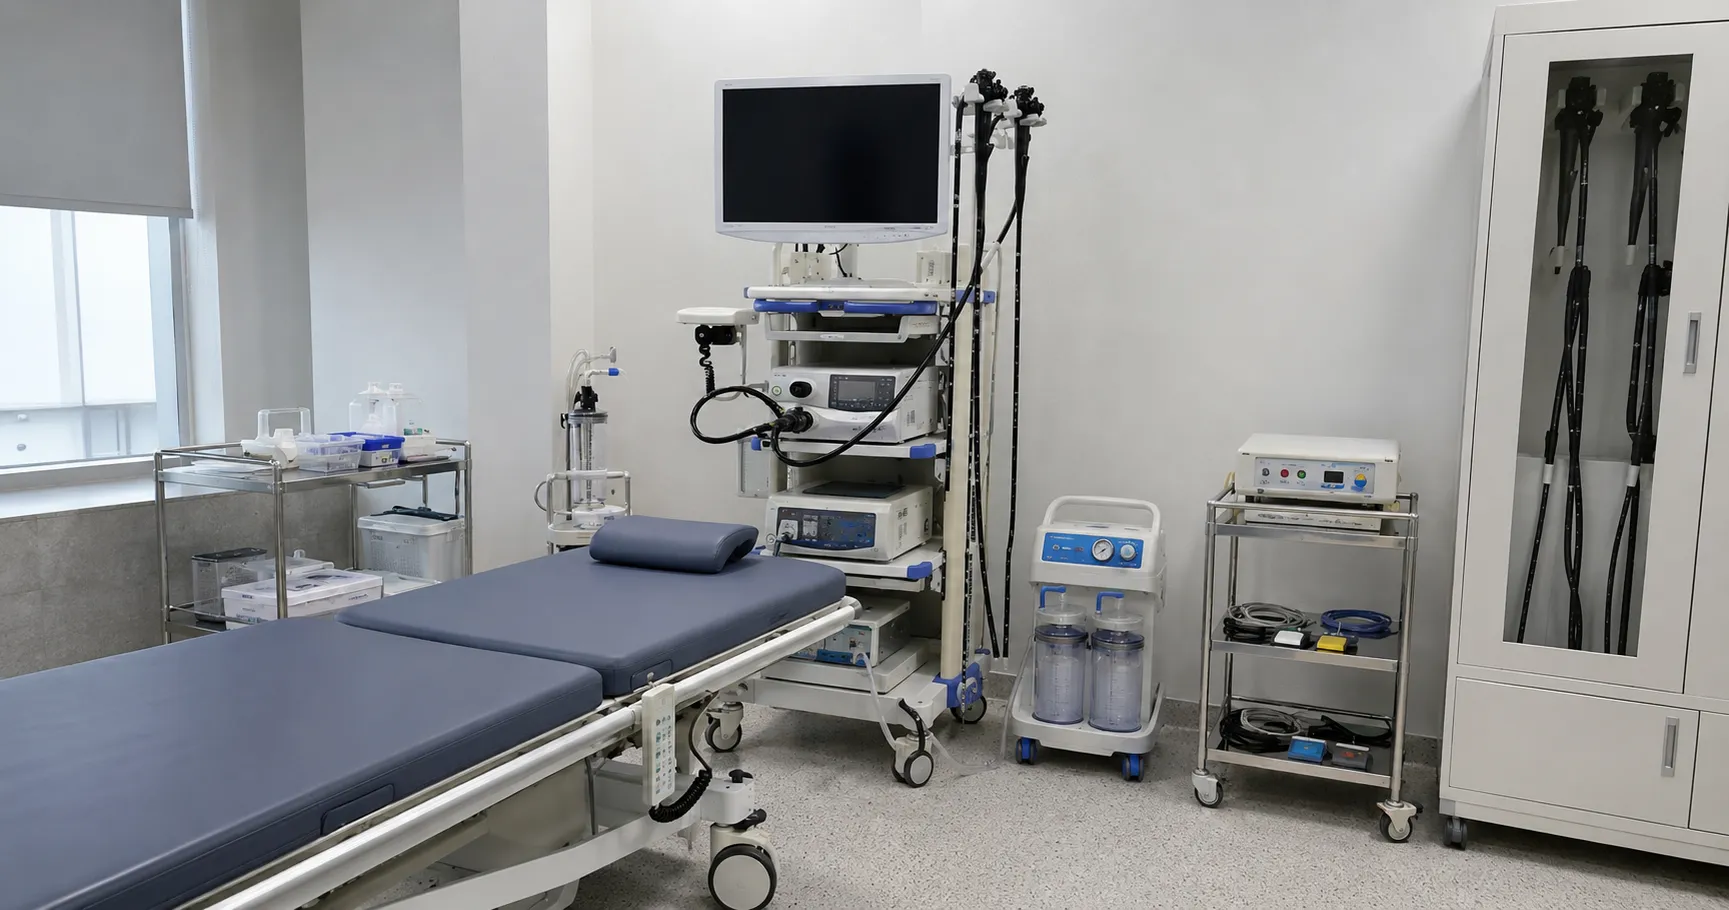
Endoscopes. Flexible endoscopes for the procedures offered — gastroscopes, colonoscopes and, where needed, bronchoscopes and specialist scopes — in enough numbers for the reprocessing cycle.
-
Endoscopy stacks. Processor, light source, monitor and image capture on a stack in each procedure room, turning the scope's view into a clear, high-definition image for the endoscopist.
-
Decontamination & reprocessing. Automated endoscope reprocessors (washer-disinfectors), drying and controlled storage cabinets, the heart of a safe unit and central to its design.
-
Procedure rooms & trolleys. Procedure trolleys or tables, positioning, and the accessories and consumables each procedure needs, arranged for a smooth, efficient list.
-
Patient monitoring & sedation. Multi-parameter monitors and oxygen for patients under sedation, with recovery-area monitoring after the procedure until sedation wears off.
-
Diathermy & therapeutic accessories. Electrosurgical units and therapeutic accessories for taking biopsies, removing polyps and treating bleeding during diagnostic and therapeutic procedures.
-
Traceability & scope tracking. A scope-tracking system that records each scope through decontamination and to the patient, for traceability, recall and audit.
-
Infrastructure. Ventilation and extraction in the decontamination area, water treatment for reprocessing, reliable power and a clear dirty-to-clean flow.
Endoscopy unit equipment checklist
|
Section |
Equipment |
Notes |
|
Scopes |
Gastroscopes; colonoscopes; specialist |
Enough for the cycle |
|
Stacks |
Processor; light; monitor; capture |
One per room |
|
Reprocessing |
Washer-disinfectors; drying/storage |
Heart of the unit |
|
Procedure |
Trolleys; positioning; accessories |
Smooth list |
|
Monitoring |
Multi-parameter monitors; oxygen |
Sedation, recovery |
|
Therapeutic |
Diathermy; biopsy/polyp accessories |
Treat and sample |
|
Traceability |
Scope-tracking system |
Recall and audit |
|
Infrastructure |
Ventilation; water; power; flow |
Dirty-to-clean |
Scale each area to your procedure volumes and case mix — a unit doing routine gastroscopy and colonoscopy and one offering complex therapeutic endoscopy differ widely in scopes, stacks and reprocessing capacity.
Planning a new endoscopy unit?
We'll help you equip it end-to-end. Tell us your procedure volumes, case mix, budget and market — we'll build the equipment list, balance new and refurbished units, and make sure everything's compliant and supported.
No pressure, no obligation. → Talk to the team
What else does setting up an endoscopy unit involve
-
Decontamination and reprocessing. Scopes are reused inside the body, so rigorous automated reprocessing, drying and controlled storage are central to the unit, not a supporting service, and shape its layout and equipping.
-
Scope numbers and cycle time. Reprocessing takes time, so a unit needs enough scopes to keep procedure rooms running while others are being cleaned and dried; scope numbers and reprocessing capacity are sized together.
-
Traceability. Each scope must be traceable through decontamination and to the patient, so a scope-tracking system is core to safety, recall and audit, not an optional extra.
-
Ventilation and water. Decontamination needs proper ventilation and extraction and treated water, so these are planned into the unit as core infrastructure from the very outset, not retrofitted.
-
Consumables, staffing and service. Accessories, detergents and reprocessing consumables, trained endoscopy and decontamination staff, and service and repair contracts all shape the running model over time, not just the purchase.
Setting up an endoscopy unit, step by step
-
Define your procedure volumes and case mix — routine diagnostic, therapeutic, specialist — and expected lists.
-
Confirm infrastructure and flow — decontamination area, ventilation, water, power and dirty-to-clean layout — and start works early.
-
Build the equipment list by area, sizing scopes and reprocessing together so cycle time does not limit your lists.
-
Decide new versus refurbished per item and plan accessory, consumable and service contracts alongside.
-
Install, commission and validate everything, prove the reprocessing, and set up scope tracking before go-live.
Reprocessing validation and scope-tracking setup take time — build them into the schedule so the unit can open safely, not just with scopes in place.
Budget and procurement
Endoscopy is capital- and consumable-intensive, so the purchase price is only part of the story; scopes, stacks, reprocessing and accessories all carry significant running and service costs. A common approach is to buy new for high-throughput core units and certified refurbished for ancillary equipment. Because these are regulated devices, check the device risk class and the certification for your market. Size scope numbers and reprocessing capacity to your busiest lists, so procedure rooms are never left waiting for a clean, dried and stored scope.
Approval and accreditation by region
|
Region |
Regulator |
Device requirement |
|
United Kingdom |
UKCA mark (CE accepted to 2028–2030) |
|
|
European Union |
CE marking under the MDR |
|
|
United States |
FDA clearance or approval |
|
|
Gulf (GCC) |
SFDA & GCC bodies |
National registration / GCC conformity |
|
South Africa |
Medical device licensing |
Endoscopes and reprocessing equipment are regulated, so confirm each is approved for your market and validated for safe reuse. Endoscope reprocessing is governed by specific decontamination standards on top of device approval, so plan for both. For quality standards and clinical guidance, the World Health Organisation and NICE are useful references. If you're equipping an endoscopy unit, our buyer hub sets out how to purchase with confidence.
More from Business
-
Buyers — source a full endoscopy unit equipment package for your hospital.
-
Suppliers — list your equipment and reach buyers worldwide.
-
Advertise — promote your products and services to a clinical audience.
-
Business overview — explore everything MediGear offers healthcare organisations.
Disclaimer
This article is for general information only and does not constitute clinical, medical, procurement, engineering or regulatory advice. Endoscopy design, equipment, reprocessing, ventilation, water and safety requirements vary by country, standard and facility, and change over time. The checklist is a general planning aid, not a specification — always work with qualified clinical, biomedical, facilities and procurement professionals, and confirm that every device is approved for your market (for example, UKCA, CE, FDA, SFDA/GCC or SAHPRA). medigear.uk accepts no liability for actions taken based on this content.
Equip your endoscopy unit end-to-end.
From endoscopes and stacks to automated reprocessors, drying cabinets and monitoring, we help hospitals across the UK, Europe, the US, the Gulf and South Africa build endoscopy units — compliant, supported and on budget.
Frequently Asked Questions
An endoscopy unit needs flexible endoscopes such as gastroscopes and colonoscopes in enough numbers for the reprocessing cycle, endoscopy stacks with processor, light and monitor in each room, automated endoscope reprocessors with drying and storage, patient monitoring for sedation, diathermy and therapeutic accessories, and a scope-tracking system. Reprocessing is as central as the scopes themselves.
The main areas are the endoscopes, the endoscopy stacks, decontamination and reprocessing, procedure rooms and trolleys, patient monitoring and sedation, diathermy and therapeutic accessories, traceability and scope tracking, and the underlying ventilation, water and power. These are planned together, because scopes are reused inside the body and must be reprocessed rigorously.
Costs depend on the procedures offered, the number of scopes and stacks, and the reprocessing capacity, so there is no single figure. Because endoscopy is consumable- and service-intensive, weigh the purchase price against running and service costs over the life of each scope and system rather than the upfront price alone.
Yes, for many items. Certified refurbished stacks and reprocessors can be sensible, provided they are fully supported and validated, while scopes are often bought new given their heavy use. Every device must be approved for your market and, for reprocessing, validated to the right standards, whether new or refurbished.
It varies with the scale and the decontamination works, but planning, installing, commissioning and validating a unit typically takes several months. The decontamination area, its ventilation and water, reprocessing validation and scope tracking are the parts most often underestimated, so build them into the schedule.
An endoscopy unit needs a decontamination area with proper ventilation and extraction, treated water for reprocessing, reliable power, and a clear dirty-to-clean flow that keeps used and clean scopes apart. This infrastructure is as central as the scopes, because safe reuse depends entirely on rigorous, validated reprocessing.