
Introduction
A high dependency unit cares for patients who are too unwell for a general ward but do not need full intensive care, so its equipment sits between the two: enhanced monitoring and organ support, without the full ventilation and one-to-one care of an ICU. Setting one up means fitting out closely monitored beds with respiratory support, infusion and resuscitation, so patients can be watched and treated more intensively as they step up from a ward or step down from intensive care.
This guide sets out the full HDU equipment list by area, the surrounding infrastructure and safety, the planning sequence, and the approval and compliance points — for a new unit, an expansion, or added level-two capacity, wherever your hospital operates. It focuses on the equipment and monitoring decisions, and flags where clinical, biomedical and estates input is essential.
What defines a high dependency unit is its place in between. It provides more monitoring and support than a ward — continuous observation, closer nursing, and the ability to support a failing system — but stops short of the full mechanical ventilation and organ support of intensive care. That makes it a step-up and step-down unit, taking deteriorating ward patients and recovering ICU patients, so it is equipped to escalate care quickly if a patient worsens and to draw on the ICU next door when full intensive care is needed. Its monitoring and support are enhanced but proportionate.
In practice, the decisions that matter most are about monitoring depth, escalation and flexibility rather than any single device. An HDU has to watch patients closely and be ready to step care up fast, so monitoring, alarms and resuscitation are planned for rapid escalation, and the unit is usually placed near intensive care. Standardising monitoring and infusion with the ICU simplifies training and patient transfers, while sizing respiratory and organ support to level-two care avoids both under-equipping and duplicating a full ICU. The result is a unit that adds real capability without becoming a second intensive care unit.
The short version — what every HDU is built around
Strip it back, and an HDU needs three things — monitoring closer than a ward, respiratory and organ support short of full intensive care, and the ability to escalate quickly.
-
Enhanced monitoring — continuous multi-parameter monitoring at every bed, closer than a ward.
-
Respiratory & organ support — oxygen, non-invasive ventilation and infusion, short of full ICU.
-
Escalation — resuscitation and the means to step care up quickly to intensive care.
HDU equipment by area
-
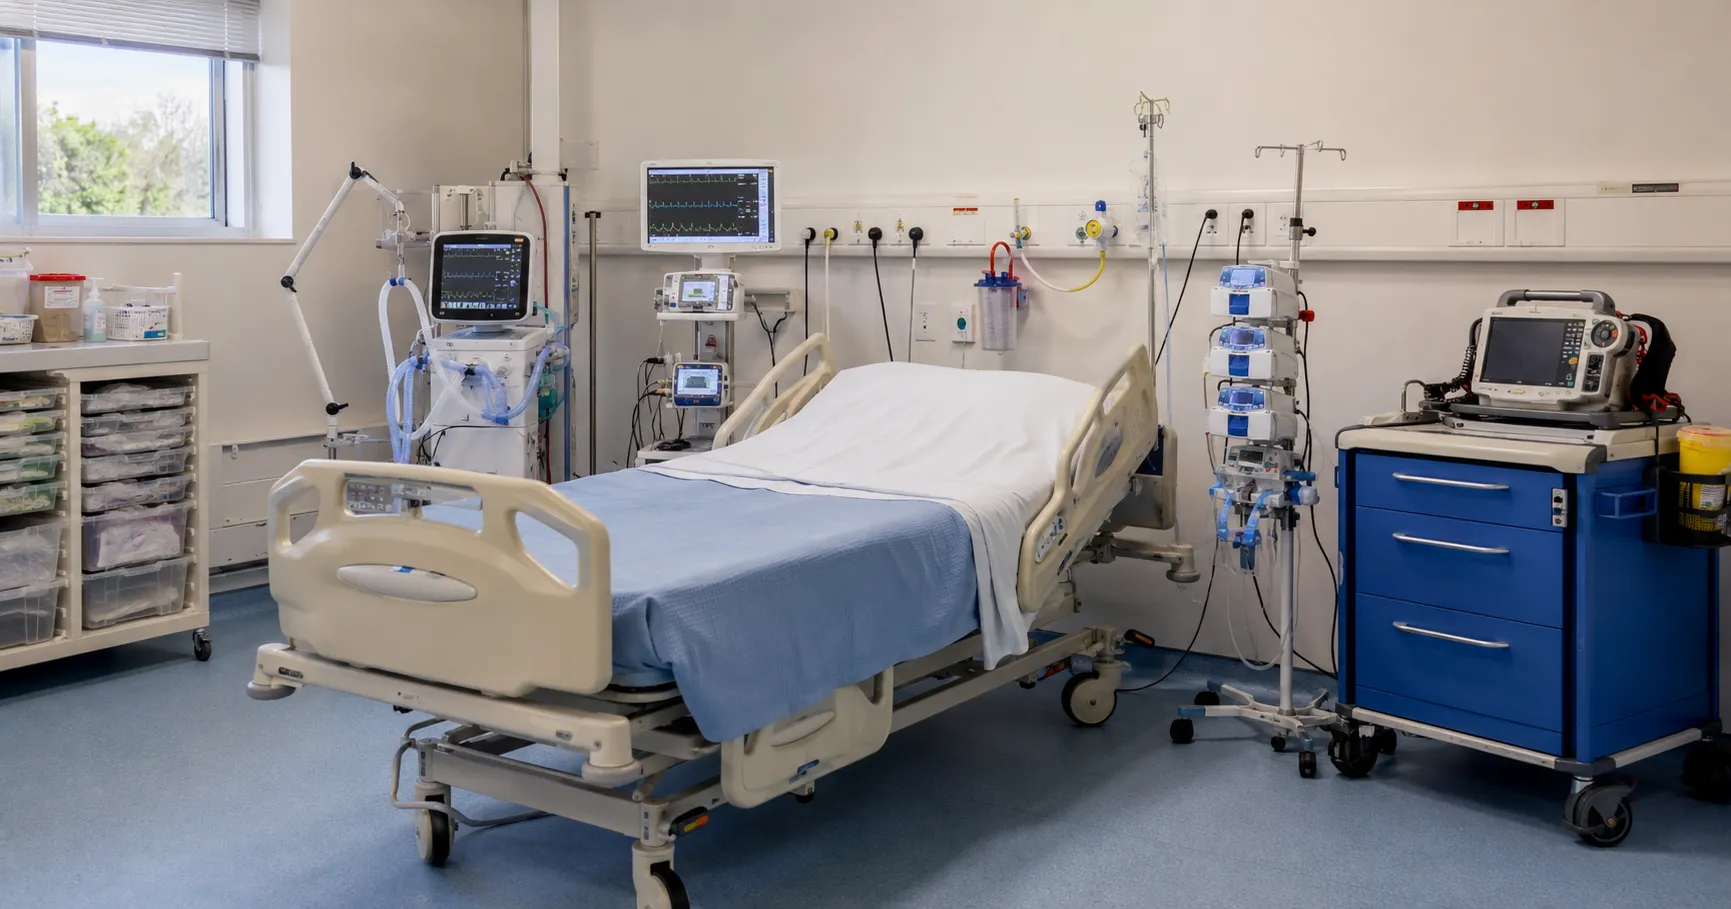
Patient monitoring. Continuous multi-parameter monitors at every bed for ECG, oxygen saturation, blood pressure and more, feeding a central station for close observation.
-
Respiratory support. Oxygen therapy, high-flow oxygen and non-invasive ventilation for patients who need breathing support without full mechanical ventilation.
-
Infusion & drug delivery. Volumetric and syringe pumps for the fluids and drugs high-dependency patients need, delivered accurately and titrated closely.
-
Resuscitation & escalation. Defibrillators and fully stocked resuscitation trolleys, ready to escalate care quickly if a patient deteriorates towards intensive care.
-
Haemodynamic monitoring. Invasive and non-invasive pressure monitoring for unstable patients, so treatment can be guided closely without full ICU support.
-
Beds & patient handling. High-dependency beds with pressure-relieving mattresses, plus hoists and transfer aids for patients who need help to move.
-
Point-of-care. Blood-gas and point-of-care testing at the bedside, so results guide treatment quickly for closely monitored patients.
-
Infrastructure. Piped medical gases, resilient power, integrated alarms, and a location and links that allow quick escalation to intensive care.
HDU equipment checklist
|
Section |
Equipment |
Notes |
|
Monitoring |
Multi-parameter monitors; central station |
Closer than a ward |
|
Respiratory |
Oxygen; high-flow; non-invasive ventilation |
Short of full ICU |
|
Infusion |
Volumetric + syringe pumps |
Titrated closely |
|
Resuscitation |
Defibrillators; crash trolley |
Escalate quickly |
|
Haemodynamic |
Invasive/non-invasive pressure |
Guide treatment |
|
Beds |
HDU beds; pressure mattresses; hoists |
Help to move |
|
Point-of-care |
Blood-gas; bedside testing |
Fast results |
|
Infrastructure |
Gases; power; alarms; near ICU |
Quick escalation |
Scale each area to your bed numbers and case mix — a general HDU and one supporting major surgery or a busy intensive care unit differ widely in monitoring and support capacity.
Planning a new HDU?
We'll help you equip it end-to-end. Tell us your bed count, case mix, budget and market — we'll build the equipment list, balance new and refurbished units, and make sure everything's compliant and supported.
No pressure, no obligation. → Talk to the team
What else does setting up a high dependency unit (HDU) involve
-
Escalation and location. An HDU must be able to step care up quickly, so monitoring, resuscitation and its position near intensive care shape the unit's design as much as any single item of equipment.
-
The right level of support. An HDU provides more than a ward but less than full intensive care, so equipment is sized to level-two care to avoid both under-equipping and duplicating a full ICU.
-
Medical gases and power. Piped oxygen and vacuum at every bed, with resilient power, are core infrastructure, since closely monitored, supported patients cannot wait for a supply that fails.
-
Standardising with the ICU. Sharing monitoring and infusion standards with intensive care simplifies training, servicing and the transfer of patients stepping up or down between the two.
-
Consumables and service. Monitors, pumps and respiratory equipment depend on a steady consumable supply and service contracts with calibration — build these into the running model, not just the purchase.
Setting up a high dependency unit (HDU), step by step
-
Define your bed count and case mix — step-up, step-down, surgical — and the level of care you will provide.
-
Confirm infrastructure and location — medical gases, power, alarms and proximity to intensive care — and start works early.
-
Build the equipment list by area, sized to level-two care, with monitoring and support proportionate to your case mix.
-
Decide new versus refurbished per item and plan consumable and service contracts alongside.
-
Install, commission and test everything, integrate monitoring and alarms, and train the team before go-live.
Monitoring integration and staff training take time — build them into the schedule so the unit can open safely, not just with equipment in place.
Budget and procurement
HDUs are equipment- and consumable-intensive, so the purchase price is only part of the story; monitors, pumps and respiratory equipment all carry running and service costs. A common approach is to buy new for high-throughput core units and certified refurbished for ancillary equipment. Because these are regulated devices, check the device risk class and the certification for your market. Match monitoring and support to level-two care and your case mix, so an HDU adds real capability without being equipped as a second, full intensive care unit.
Approval and accreditation by region
|
Region |
Regulator |
Device requirement |
|
United Kingdom |
UKCA mark (CE accepted to 2028–2030) |
|
|
European Union |
CE marking under the MDR |
|
|
United States |
FDA clearance or approval |
|
|
Gulf (GCC) |
SFDA & GCC bodies |
National registration / GCC conformity |
|
South Africa |
Medical device licensing |
High-dependency devices are regulated, so confirm each is approved for your market. HDU equipment supports closely monitored, unstable patients, so approval, servicing and readiness all matter to keep a bed safe. For quality standards and clinical guidance, the World Health Organisation and NICE are useful references. If you're equipping a high dependency unit (HDU), our buyer hub sets out how to purchase with confidence.
More from Business
-
Buyers — source a full high dependency unit equipment package for your hospital.
-
Suppliers — list your equipment and reach buyers worldwide.
-
Advertise — promote your products and services to a clinical audience.
-
Business overview — explore everything MediGear offers healthcare organisations.
Disclaimer
This article is for general information only. It is not clinical, medical, procurement, engineering or regulatory advice. High dependency unit design, equipment, infrastructure, staffing and safety requirements vary by country, level of care and facility, and change over time. The checklist is a planning aid, not a specification. Always work with qualified clinical, biomedical, facilities and procurement professionals. And confirm every device is approved for your market — for example, UKCA, CE, FDA, SFDA/GCC or SAHPRA. Requirements change, so check the current position before you buy. medigear.uk accepts no liability for actions taken on this content.
Equip your HDU end-to-end.
From multi-parameter monitors and non-invasive ventilation to infusion pumps and resuscitation equipment, we help hospitals across the UK, Europe, the US, the Gulf and South Africa build high dependency units — compliant, supported and on budget.
Frequently Asked Questions
An HDU needs continuous multi-parameter monitoring at every bed, respiratory support such as high-flow oxygen and non-invasive ventilation, volumetric and syringe infusion pumps, defibrillators and resuscitation trolleys, invasive and non-invasive haemodynamic monitoring, high-dependency beds, and point-of-care testing — on resilient gases and power. It provides more than a ward but less than full intensive care.
The main areas are patient monitoring, respiratory support, infusion and drug delivery, resuscitation and escalation, haemodynamic monitoring, beds and patient handling, point-of-care testing, and the underlying gases, power and alarms. These are planned together, and usually near intensive care, because an HDU must escalate care quickly.
Costs depend on the number of beds, the case mix and how much monitoring and support each bed needs, so there is no single figure. Because HDUs are consumable- and service-intensive, weigh the purchase price against running and service costs over the life of each device rather than the upfront price alone.
Yes, for many items. High-use core devices such as monitors are often bought new, while certified refurbished units can be sensible for beds, pumps and ancillary equipment. Every device must be approved for your market and fully supported with service and consumables, whether new or refurbished.
It varies with the scale and whether infrastructure works are needed, but planning, equipping, commissioning and training typically take several months. Medical-gas and power works, monitoring integration and staff training are the parts most often underestimated, so build them into the schedule from the start.
An HDU needs piped medical gases at every bed, resilient power, integrated monitoring and alarms, and a location near intensive care so care can be escalated quickly. This infrastructure is as important as the clinical equipment, because high-dependency patients are closely monitored and may deteriorate and need intensive care.