
Introduction
The intensive care unit is where connected equipment matters most and forgives least. Patients here are continuously monitored, treated with several devices at once, and watched around the clock, so the case for connection is obvious — and so is the cost of getting it wrong. This buyer's guide is written for the teams choosing IoT equipment for the ICU: what to look for, what to question, and where the real decisions lie. It applies wherever you work, from the UK and Europe to the US, the Gulf and South Africa.
Why the ICU is different
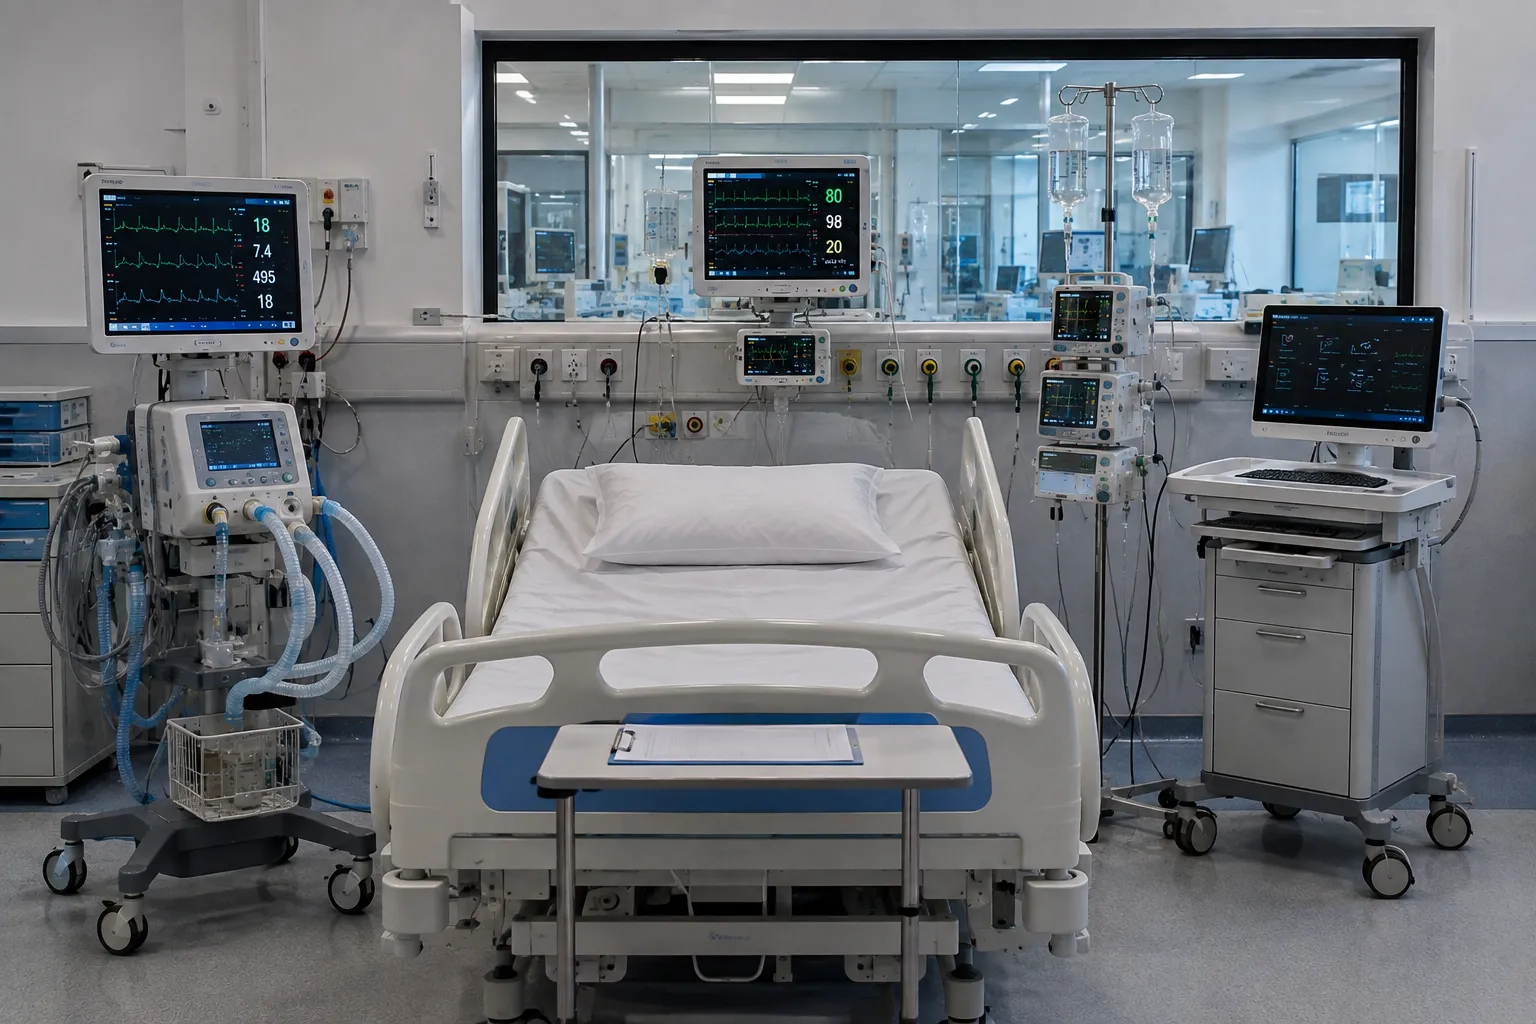
In a general ward, a device that drops offline for a moment is an inconvenience. In intensive care, the same gap can matter a great deal, because the equipment is often the difference between knowing a patient's state and guessing at it. The ICU also crowds many devices around one bed — ventilators, monitors, pumps — which means they must not only work but work together, feeding a single clear picture rather than a wall of separate screens. A higher standard, therefore, judges connection in the ICU: it has to be reliable, coherent, and secure all at once.
The ICU buyer's checklist
-
Does it integrate at the bedside? Devices should combine into a single view, not force staff to read across several screens under pressure.
-
Is it approved and reliable? ICU equipment must be properly regulated, well documented and dependable without exception.
-
Can it be kept secure for its whole life? Connected ICU devices need built-in security and a clear commitment to updates.
-
Are alarms manageable? Intensive care is prone to alarm overload; good equipment lets warnings be tuned so they still mean something.
-
What support stands behind it? Service, spares and response times are part of the purchase, not an extra.
Interoperability is the deciding factor.
More than anywhere else, the ICU depends on devices from different makers working as one. That only happens if they share recognised standards. Work such as the ISO/IEEE 11073 family for point-of-care medical device communication exists precisely so that intensive care equipment can exchange data through a common language rather than a tangle of proprietary links. For a buyer, the practical rule is blunt: a device that cannot connect on open, recognised standards may be brilliant on its own and still a poor fit for a connected ICU, because it cannot join the shared picture the unit runs on.
Standalone ICU kit versus connected ICU kit
|
Standalone ICU equipment |
Connected ICU equipment |
|---|---|
|
Each device on its own screen |
One combined bedside picture |
|
Data recorded by hand |
Data flows into the record |
|
Proprietary, closed links |
Open, recognised standards |
|
Watched only at the bedside |
Visible across the unit |
Security cannot be an afterthought
A connected ICU device sits on the hospital network and handles a critically ill patient's data, which makes its security a clinical matter, not merely an IT one. Regulators now treat protection as part of a device's safety: the FDA treats cybersecurity as part of medical device safety, expecting it to be built in and maintained across the device's life. For an ICU buyer, that means asking hard questions before purchase — how the device is protected, how it is updated, and for how long — and treating a device that cannot be kept secure as one that does not belong on the unit.
What to weigh before you commit
-
Fit with your existing systems. Confirm the device joins your current ICU picture rather than standing apart from it.
-
The whole-life view. Weigh updates, support and spares over years, not just the day-one specification.
-
Documentation and approval. Insist on properly regulated, well-documented equipment with a clear provenance.
-
Human factors. Under pressure, clarity saves time; test how the device actually reads and behaves at the bedside.
The bottom line
Buying IoT equipment for the ICU is a higher-stakes version of every connected-device decision a hospital makes. The prizes — a single clear picture of the sickest patients, continuous data, faster response — are larger, and so are the penalties for reliability, interoperability or security done badly. The buyer's task is to look beyond the individual device to how it will fit into a connected unit: whether it joins the shared picture on open standards, whether it can be kept secure for years, and whether sound hardware and reliable support stand behind it. Get those right, and connection makes intensive care safer. Get them wrong, and it adds risk exactly where a hospital can least afford it.
More from Business
-
Buyers — source approved, well-documented equipment.
-
Suppliers — list your equipment and reach buyers worldwide.
-
Advertise — promote your products and services to a clinical audience.
-
Business overview — explore everything MediGear offers healthcare organisations.
Disclaimer
This article is for general information only and does not constitute clinical, procurement, regulatory, security or legal advice. IoT equipment for the intensive care unit and the standards and rules that govern them are evolving, and requirements vary by market and change over time. Cybersecurity and interoperability requirements should always be confirmed with the relevant authorities. Always consult qualified clinical, biomedical engineering, information governance and security professionals for decisions specific to your organisation. medigear.uk accepts no liability for actions taken based on this content.
Equip a connected ICU.
Genuine, approved, fully documented medical equipment — the reliable hardware a smart, connected hospital is built on, wherever you work.
Frequently Asked Questions
The stakes are higher and the tolerance for error lower. ICU patients are monitored continuously and treated with several devices at once, so equipment must not only work reliably but work together, feeding a single clear picture rather than a wall of separate screens. Connection in intensive care is judged by stricter standards of reliability, coherence, and security than those a general ward would require.
Bedside integration into one view, proper regulatory approval and reliability, whole-life security with a clear update commitment, manageable and tunable alarms, and real support with spares and response times. Each of these is essential in intensive care, where a gap in any one can matter a great deal.
Because the unit depends on devices from different makers working as one, that only happens if they share recognised standards, such as the ISO/IEEE 11073 family for point-of-care device communication. A device that cannot connect to open standards may be excellent on its own yet a poor fit for a connected ICU, because it cannot join the shared picture the unit runs on.
It is a clinical matter, not just an IT one. A connected ICU device sits on the hospital network and handles a critical patient's data. Regulators now treat protection as a device's safety, expecting it to be built in and maintained throughout the device's life. A device that cannot be kept secure does not belong on the unit.
By choosing equipment whose alarms can be sensibly tuned. Intensive care is especially prone to alarm fatigue, where constant alerts train staff to tune them out. Good connected equipment lets warnings be configured so they remain meaningful and proportionate, which is an important test when comparing devices.
Look past the individual device to how it will fit into a connected unit: whether it joins your existing ICU picture on open standards, whether it can be kept secure for years, whether it is properly approved and well-documented, and how it actually reads and behaves at the bedside under pressure. The whole-life view of updates, support and spares matters as much as the day-one specification.